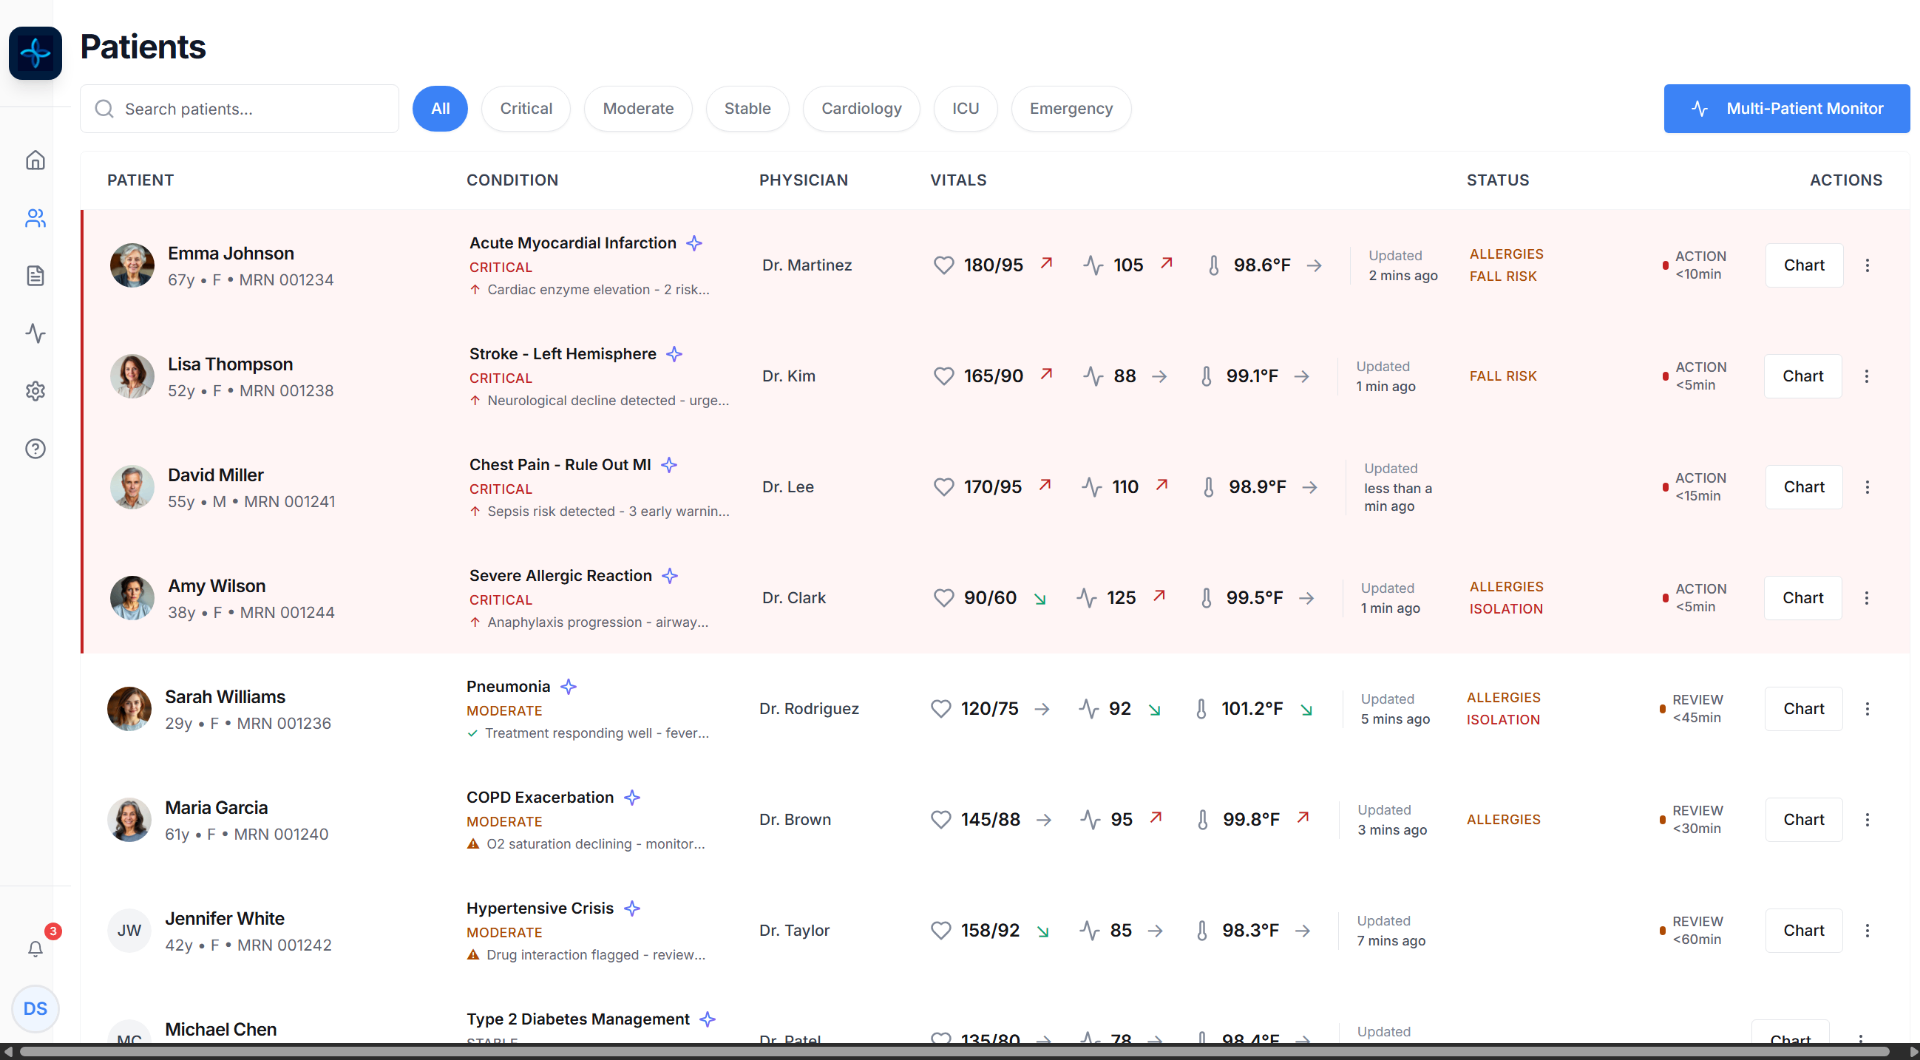
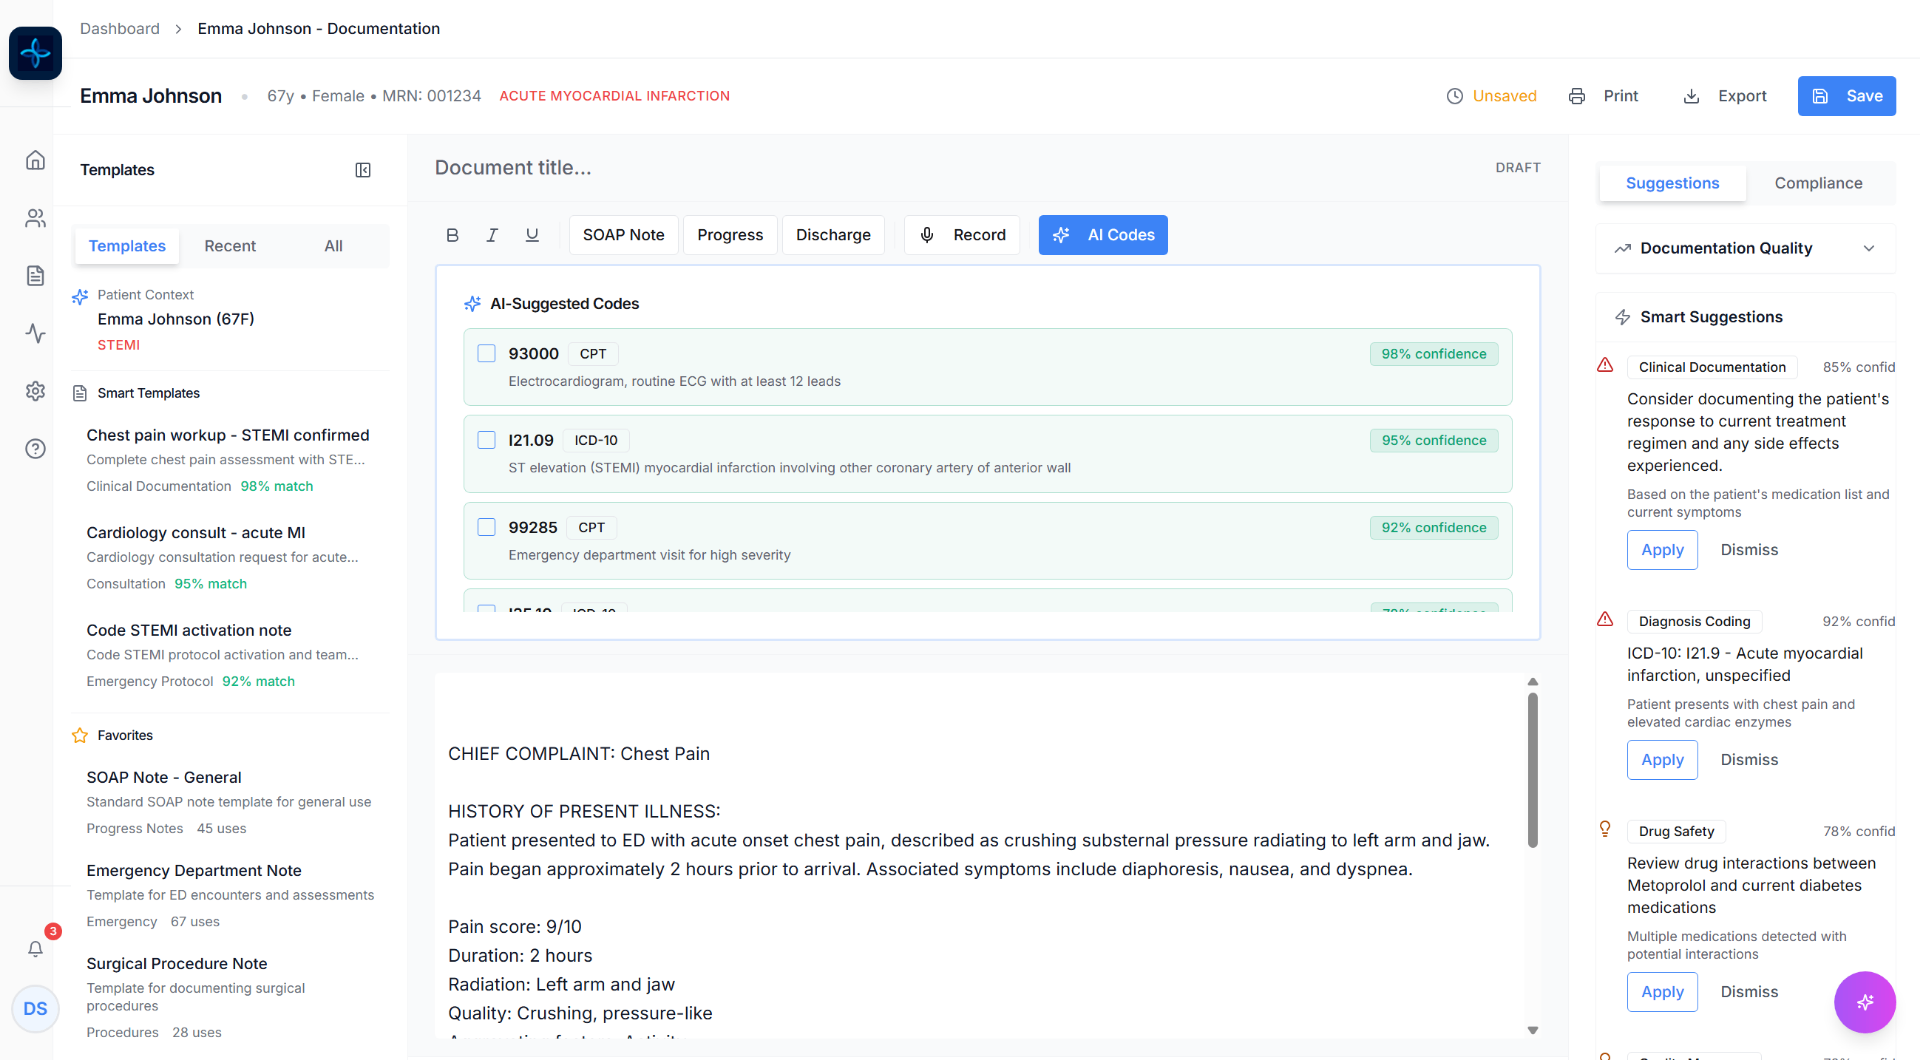
Physician Reaction
We showed the prototype to Dr. Chen first.
Her reaction:
"Oh. OH. This is actually useful. This is how I think through a diagnosis anyway. I'm just getting a second opinion from someone who's read every case study ever published. I can work with this."
Week 4: Converting the Chief Skeptic
We arranged a design session with Dr. Jennings. We asked him to walk through a complex radiology case using the current system.
What did the chief skeptic object to?
He pulled up a chest scan. The AI flagged it: "92% probability of malignancy."
His response: "See? Useless. Is it Stage 1 or Stage 4? Where specifically? What am I looking at? This tells me nothing I can act on."
What did we change in response?
We showed him our redesigned version:
- •Specific location marked on the scan with measurement overlay
- •Growth pattern analysis compared to previous scans (new finding, grew 3mm in 2 months)
- •Similar case references from medical literature
- •Suggested protocol: Biopsy recommended, staging CT scan
- •Override option: "Clinical judgment indicates further monitoring" with documentation field
How did the skeptic come around?
Dr. Jennings studied it carefully. Then:
"This... this I can use. You're showing me exactly what I need to see and documenting why I made my decision either way. This protects me legally and makes me more efficient clinically. Why didn't the original system do this?"
That was the turning point. When the chief skeptic became an advocate, momentum shifted.
The Design Process (4 Months from Discovery to Implementation)
Week 1-2: Rapid Research
- •Shadowed 23 physicians across specialties
- •Recorded clinical workflow sessions (with permission)
- •Used Claude to analyze 50+ workflow transcripts in 2 days (vs 3 weeks manual coding)
- •Identified 12 distinct decision patterns physicians actually used
Key Insight
Physicians think in differential diagnoses, not probability scores. They're running mental algorithms. We just needed to externalize that process.
Week 3-4: Rapid Prototyping
- •Generated 15 interface variations using AI-accelerated design
- •Each showed different ways to visualize clinical reasoning
- •Tested concepts weekly with physicians instead of waiting for polished designs
Dr. Torres after seeing Version 7: "Getting warmer. But flip these panels. I look at vitals before imaging in my mental process."
Week 5-8: Functional Testing
- •Built working prototype using Lovable
- •Real physicians tested with real cases during actual shifts
- •Feedback loop: observe in morning, revise in afternoon, test next morning
- •Made 34 substantive changes based on real-world use
Week 9-16: Progressive Rollout
- •Started with 5 champion physicians
- •Their success stories convinced the next 15
- •Word spread organically through the medical staff
- •Network effects took over
What Worked (And the Metrics That Proved It)
"Show Your Work" Transparency
Making the AI explain its reasoning reduced physician anxiety significantly (measured through pre/post surveys).
Dr. Patel: "I don't feel like I'm blindly following orders. I'm consulting with a colleague who has perfect recall of thousands of cases."
Progressive Disclosure Design
- •Simple view for routine cases (pneumonia, UTI, common diagnoses)
- •Detailed analysis mode for complex or rare presentations
- •Physicians could drill down when needed or trust the summary when comfortable
The "Override and Document" Feature
This became the key trust-builder. Physicians could disagree with AI recommendations but had to document their clinical reasoning.
Dr. Chen: "Brilliant. It's not forcing me to follow AI. It's asking me to articulate my clinical reasoning, which is good medicine whether the AI is right or wrong. The documentation becomes valuable regardless."
Result: Override documentation became both legal protection AND valuable training data for improving the AI.
Seamless Workflow Integration
- •No separate app or login required
- •Embedded directly in the EMR they already used
- •Appeared at the exact workflow moment where diagnostic decisions were made
- •Added 47 seconds average to documentation time
- •Saved 12 minutes in diagnostic research time
Adoption Results (8 Weeks Post-Launch)
11% → 68%
Physician adoption
47%
AI recommendations influencing treatment
23%
Reduction in unnecessary tests
Zero
Malpractice complaints
What did the project teach us?
1. Medical Intuition Follows Structure, Just Very Quickly
We initially thought physicians made intuitive leaps. Actually, they follow structured reasoning that's so well-practiced it feels intuitive. Once we understood the structure, we could design for it.
Dr. Jennings explained: "When I look at a scan, I'm running through a mental checklist built from 40 years of pattern recognition. Your design externalized that checklist. That's why it works. It matches how I actually think."
2. Language and Tone Matter More Than Expected
Our initial prototypes used clinical textbook language. It felt sterile and alienating.
When we switched to conversational medical language, how physicians actually talk to colleagues, engagement improved dramatically.
Before:
"Radiographic evidence suggests neoplastic process"
After:
"This pattern typically indicates cancer, but let's rule out infection first"
3. Physicians Want to Be Enhanced, Not Replaced
The framing was critical. Not "AI will diagnose for you" but "AI gives you instant access to insights from 100,000 similar cases."
Dr. Torres: "I went to medical school to make good clinical decisions, not to memorize every rare presentation of every disease. This makes me better at my actual job."
4. Liability Concerns Drove Every Design Decision
Every feature had to answer: "Can I defend this choice in court?"
The AI explanation interface wasn't optional. It was the entire value proposition. Without it, nothing else mattered.
What makes clinical AI harder to design?
01
Medical-Legal Liability Shaped Every Design Choice
- •Had to show AI reasoning for defensive medicine purposes
- •"I don't know" option was crucial: AI admitting uncertainty built more trust than false confidence
- •Override documentation became legal protection for physicians
02
HIPAA Compliance Limited Data Visualization
- •Couldn't show similar patient cases with identifying details
- •Had to anonymize all reference examples
- •Limited comparative data display options
Technical Constraint:
All patient data references required anonymization before display
03
Clinical Workflow Interruption Could Cost Lives
- •Timing of AI suggestions was critical: wrong moment = ignored
- •Had to account for ED chaos vs. scheduled clinic visits vs. ICU monitoring
- •Emergency override path required (cardiac arrest doesn't wait for AI explanation)
Technical Constraint:
System must adapt to different clinical contexts and allow instant dismissal in emergencies
04
Physicians Think in Differential Diagnoses, Not Linear Flows
- •Had to support parallel consideration of multiple conditions
- •Simple decision trees didn't match clinical reality
- •Interface needed to support "what if" exploration without commitment
Technical Constraint:
UI must display multiple diagnostic pathways simultaneously without forcing linear progression
Non-Linear Diagnostic Reasoning
Traditional software assumes linear decision-making: A leads to B leads to C. Medical diagnosis doesn't work that way.
Physicians consider multiple possibilities simultaneously, weighing evidence that supports or contradicts each hypothesis in parallel.
•All evaluated SIMULTANEOUSLY, not sequentially
•Evidence flows between branches
•This is why simple decision trees failed
•Interface must support parallel consideration
× Traditional: Pick A → then B → then C
✓ Physicians: Consider A, B, C, D simultaneously
Our solution: Interface mirrors non-linear reasoning
What changed after launch?
6 Months After Launch
Adoption Metrics
68%
physician adoption (from 11%)
✓
System now regularly cited in clinical documentation
3
Department heads who initially resisted now requesting expansion
Zero
AI-related concerns in legal team chart reviews
Clinical Impact
23%
reduction in unnecessary diagnostic testing
47%
of AI recommendations actively inform treatment decisions
8 min
average diagnostic time reduced per complex case
The Most Telling Sign
Last month the system went down for maintenance. The help desk was flooded with calls.
"Is the AI coming back up soon? I'm flying blind here."
Dr. Chen's message
That's when you know adoption is real.
Team Reflections
"We spent $2 million on technology and got 11% adoption. We invested $45,000 in 32°N's redesign and got 68% adoption. The technology was never the problem. The interface was. Sometimes the best technology investment is making existing technology actually usable."
Dr. Robert Jennings
Chief of Radiology
"I fought this system hard initially. Not because I'm anti-technology, but because my concerns weren't being addressed. This redesign took those concerns seriously. The result is a tool that makes me a better radiologist, not a redundant one."
"The unexpected benefit? Residents are learning better. They see the AI reasoning, watch attendings override with documented logic, and they're learning systematic clinical thinking. It became a teaching tool we didn't plan for."
Project Credits
Client
Memorial Regional Hospital
Timeline
4 months (design and implementation)
32°N Team
Lead UX Designer, Healthcare UX Specialist, AI Integration Designer
Collaboration
Hospital IT team, Clinical advisory board (15 physicians), Legal review team
Technology
Existing AI diagnostic system, EMR integration (Epic), Custom explanation interface layer
The 32°N Difference
This case study demonstrates Thirty Two North's approach to healthcare AI adoption: technology adoption isn't about features. It's about trust. And trust requires transparency that matches how professionals actually think and work.
By completing this transformation in just 4 months, versus the typical 12+ month redesign cycle, we helped Memorial Regional turn a $2M underperforming investment into a genuinely valuable clinical tool. Our AI-accelerated research and design process, combined with deep healthcare domain expertise, delivered both speed and deep understanding of clinical workflows.
The result: A 518% increase in physician adoption and a system that doctors now miss when it's unavailable.
Hospital name, physician names, and some identifying details have been changed to maintain patient privacy and confidentiality. All design decisions, technical implementations, adoption metrics, and clinical outcomes described are accurate representations of the actual project. The AI diagnostic interface and its explanation capabilities are live and in active clinical use.